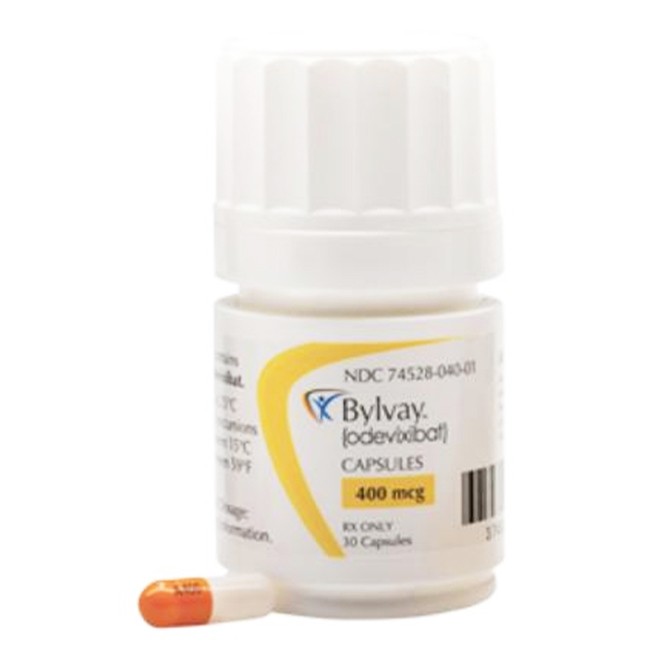
Odevixibat is used to treat pruritus in patients with PFIC and ALGS. Its absorption and efficacy are affected by diet, and it may interfere with the absorption of fat-soluble vitamins. Patients should pay attention to the following dietary considerations.
I. Coordination of Medication and Meals
1. Take with Meals
Odevixibat should be taken in the morning with a meal to align with the physiological rhythm of bile acid transport.
Taking it with a meal helps the drug fully exert its IBAT inhibitory effect in the intestine.
A high-fat meal reduces the peak plasma concentration and exposure of odevixibat, but this effect is not considered clinically significant.
Maintaining regular meals is still recommended to avoid affecting medication adherence by deliberately changing dietary structure.
2. Interval with Bile Acid Binding Resins
If patients are also taking bile acid binding resins such as cholestyramine, colesevelam, or colestipol, attention should be paid to the dosing interval.
Odevixibat should be taken at least 4 hours before or at least 4 hours after bile acid binding resins.
Bile acid binding resins may bind odevixibat in the gut and reduce its efficacy.
Reasonably arranging the administration time of these two types of drugs is an important dietary-related measure to ensure efficacy.
II. Preparation and Administration of Oral Pellets
1. Soft Food Mixing Method
Oral pellets can be administered by mixing into a small amount of soft food, such as applesauce, oatmeal, banana or carrot puree, chocolate or rice pudding.
Soft food should be kept at room temperature or cooler to avoid overheating affecting drug stability.
After gently mixing the pellets with soft food until evenly dispersed, the entire dose should be administered immediately and should not be stored for later use.
After administration, breast milk, infant formula, or other age-appropriate liquids may be given.
2. Liquid Administration Method
For patients unable to swallow soft food, oral pellets may be mixed with an appropriate amount of liquid and administered using an oral syringe.
The liquid may be breast milk, infant formula, or water. After adding, let it sit for approximately 5 minutes to allow the pellets to become fully wetted.
The pellets will not dissolve in the liquid. Repeatedly draw up and push back 2 to 3 times to ensure complete mixing.
Do not administer via a bottle or sippy cup because the pellets cannot pass through the opening and will not dissolve.
After administration, check the child's mouth to confirm that all liquid and pellets have been swallowed.
III. Monitoring and Supplementation of Fat-Soluble Vitamins
1. Deficiency Risk and Monitoring
Odevixibat may affect the absorption of fat-soluble vitamins A, D, E, and K.
Patients with PFIC and ALGS may already have fat-soluble vitamin deficiency and often require long-term supplementation.
Baseline serum fat-soluble vitamin levels should be obtained before treatment and monitored regularly during treatment.
Vitamin K status can be assessed by INR, and clinical manifestations should also be monitored.
2. Supplementation and Dietary Adjustment
If fat-soluble vitamin deficiency is diagnosed, timely supplementation should be provided.
If deficiency persists or worsens despite adequate supplementation, permanent discontinuation of odevixibat should be considered.
If complications of fat-soluble vitamin deficiency occur, treatment interruption should be considered and the adequacy of supplementation should be reassessed.
Patients may bleed more, bleed longer, or experience fractures, and should seek medical attention promptly if related symptoms occur.
Foods rich in fat-soluble vitamins may be appropriately increased in the daily diet, but the use of supplements should follow medical advice.

Free Inquiry