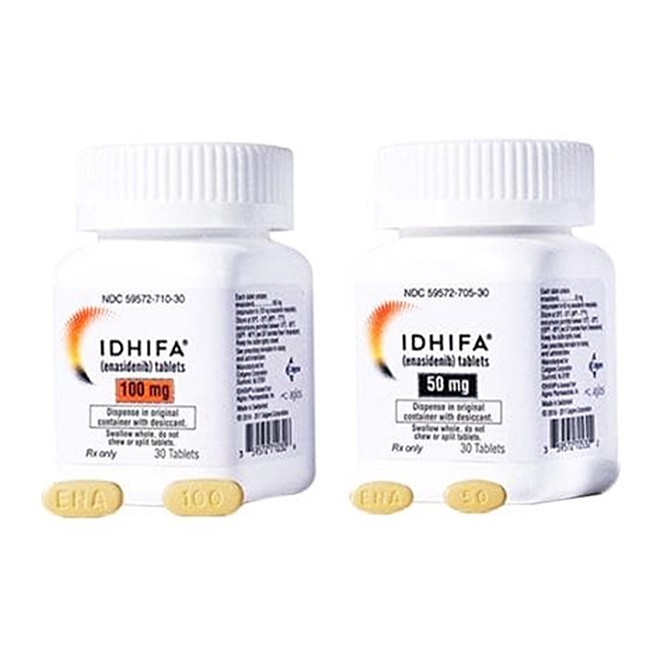
Enasidenib is used for IDH2-mutant acute myeloid leukemia, and medication in special populations requires extra caution. The following explains key precautions in three aspects.
I. Medication for Pregnant and Breastfeeding Women
1. Pregnancy: Clearly Contraindicated
Enasidenib can cause fetal harm. Animal studies show that administration during pregnancy can cause embryo death, growth retardation, and skeletal variations. Women of reproductive potential must undergo pregnancy testing before starting treatment. If pregnancy occurs or is suspected during treatment, inform the doctor immediately.
2. Lactation: Breastfeeding Prohibited
It is currently unknown whether enasidenib enters breast milk. Due to the potential for serious adverse reactions in breastfed infants, breastfeeding should be stopped during treatment and for 2 months after the last dose.
3. Contraception Requirements
Women of reproductive potential should use effective non-hormonal contraception during treatment and for 2 months after the last dose. Enasidenib may reduce the effectiveness of hormonal contraceptives, so those using hormonal contraception should switch to non-hormonal methods.
II. Men of Reproductive Potential and Fertility Effects
1. Contraception Recommendations for Men
Male patients whose female partners have reproductive potential should use effective contraception during treatment and for 2 months after the last dose to avoid potential risk to the fetus.
2. Potential Effects on Fertility
Animal studies suggest that enasidenib may impair fertility in both women and men. It is currently unknown whether this effect is reversible. If there are fertility plans, communicate fully with the doctor before treatment.
3. Consultation Before Medication
Both men and women of reproductive potential should understand the potential effects of the drug on fertility before starting treatment. If necessary, consider fertility preservation consultation in advance.
III. Medication for Pediatric and Elderly Patients
1. Pediatric Patients: Not Yet Established
The safety and effectiveness of enasidenib in pediatric patients have not been established, and it is not recommended for pediatric use.
2. Elderly Patients: No Dose Adjustment Needed
In clinical studies, most patients were over 65 years old, and some were over 75. No overall differences in effectiveness or safety were observed between elderly and younger patients, so dose adjustment based solely on age is not needed.
3. Individualized Monitoring
Elderly patients often have other diseases or medications. During treatment, monitoring of blood counts, liver function, etc. should be strengthened to promptly detect and manage adverse reactions.
IV. Patients with Hepatic or Renal Impairment
1. Hepatic Impairment
Mild, moderate, and severe hepatic impairment have no clinically significant effect on the pharmacokinetics of enasidenib. However, bilirubin and liver function should still be monitored regularly during treatment, and drug-related bilirubin elevation should be watched for.
2. Renal Impairment
Mild to moderate renal impairment (creatinine clearance ≥30 mL/min) requires no dose adjustment. Data are limited for patients with severe renal impairment or on dialysis, so use should be cautious under medical guidance with enhanced monitoring.
3. Medication Principles
Patients with hepatic or renal impairment do not require routine dose reduction, but adverse reactions should be closely observed. If necessary, adjust the dose or suspend medication according to toxicity grading.

Free Inquiry