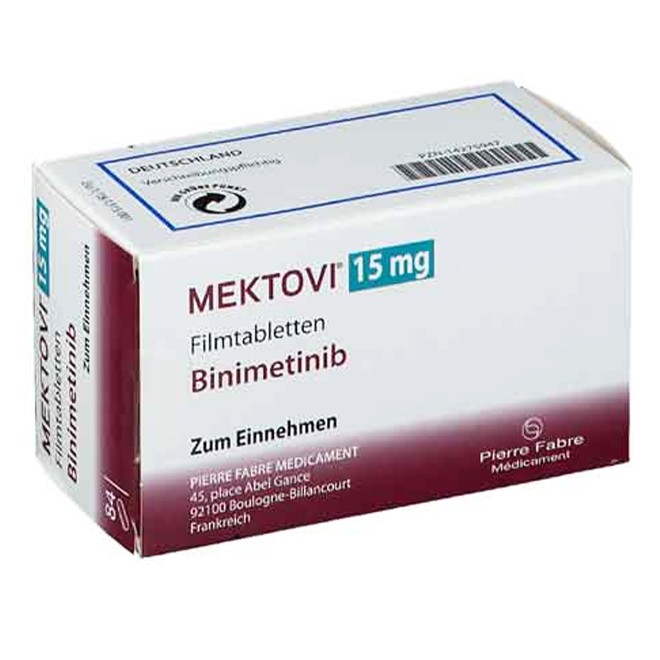
Binimetinib is often used in combination with encorafenib for the treatment of BRAF mutation-positive tumors. Understanding its contraindications and adverse reactions helps ensure safe medication use and timely management.
I. Contraindications and precautions before use
1. No absolute contraindications
No absolute contraindications are listed in the binimetinib prescribing information. However, before use, it should be confirmed that the patient does not have specific high-risk conditions, and the doctor should comprehensively assess the benefits and risks.
2. Patients with limited cardiac function
Safety has not been established in patients with a left ventricular ejection fraction below 50% or below the institutional lower limit of normal. Medication use in such patients requires particular caution, and cardiac function should be assessed before treatment.
3. Patients with a history of retinal vein occlusion
Safety has not been established in patients with a history of retinal vein occlusion or with risk factors such as uncontrolled glaucoma, hyperviscosity syndrome, or hypercoagulable states, and use should be avoided or closely monitored.
4. Restrictions on combination use with encorafenib
Binimetinib must be used in combination with encorafenib. If encorafenib is permanently discontinued due to adverse reactions, binimetinib should also be discontinued. Relevant risk information in the encorafenib prescribing information should be reviewed before use.
II. Common adverse reactions
1. Systemic and gastrointestinal reactions
The most common are fatigue, nausea, diarrhea, vomiting, and abdominal pain. These reactions may affect eating and daily life, and dose adjustment or temporary discontinuation may be necessary.
2. Skin and visual reactions
Rash, dry skin, and itching may occur. Visual effects include blurred vision, visual impairment, and serous retinopathy, and some patients require ophthalmologic examination or dose adjustment.
3. Other common reactions
These include constipation, dyspnea, cough, musculoskeletal pain, dizziness, hypertension, peripheral edema, fever, and decreased appetite. The reaction profile differs slightly among patients with different tumor types.
III. Serious adverse reactions and monitoring
1. Cardiotoxicity
It may present as left ventricular dysfunction or heart failure. Ejection fraction should be assessed before treatment, one month after treatment initiation, and regularly thereafter. Symptomatic heart failure or a significant decrease in ejection fraction requires permanent discontinuation.
2. Thrombosis and bleeding
Deep vein thrombosis, pulmonary embolism, and bleeding in the gastrointestinal tract, intracranial area, and other sites may occur. Sudden difficulty breathing, leg pain or swelling, or abnormal bleeding requires immediate medical attention. Life-threatening pulmonary embolism or intracranial hemorrhage requires permanent discontinuation.
3. Serious ocular toxicity
Once retinal vein occlusion is confirmed, binimetinib must be permanently discontinued. Serous retinopathy and uveitis require temporary discontinuation, dose reduction, or discontinuation depending on severity, along with regular ophthalmologic assessment.
4. Hepatotoxicity
It may cause elevated transaminases and alkaline phosphatase. Liver function should be monitored regularly before and during treatment, and jaundice, dark urine, fatigue, or bleeding tendency should be reported promptly.
5. Rhabdomyolysis
It may present as elevated creatine kinase, with or without muscle pain, weakness, or dark urine. Creatine kinase and creatinine should be monitored regularly during treatment, and temporary discontinuation or discontinuation is required in severe cases.
6. Interstitial lung disease
New or worsening cough or dyspnea should prompt evaluation for interstitial lung disease. After confirmation, temporary discontinuation, dose reduction, or permanent discontinuation is required depending on severity.
7. New primary malignancies
Cutaneous and non-cutaneous new primary malignancies may occur with combination use with encorafenib. The skin and other suspicious symptoms should be monitored before treatment, during treatment, and after discontinuation.
8. Embryo-fetal toxicity
Binimetinib can cause fetal harm. Women of reproductive potential should use effective contraception during treatment and for at least 30 days after the last dose. Use during pregnancy requires informing of the fetal risk.

Free Inquiry